An implant invoice is the supplier's invoice showing what a hospital paid for a device implanted in a patient, such as a pedicle screw, a lens, a stent or a joint component, and insurers ask for it when the contract pays implants at cost plus a markup or when the billed implant charge needs proving. On a hospital bill, the device appears as a charge line with a revenue code, a device code and a unit count; in the medical record, it appears in the implant log of the operative report, often scanned from the package at the table. A health plan's reviewer reconciles all three: the invoice, the log and the billed line. Botminds' Itemized Bill Review does that reconciliation on every implant line of every bill over the plan's threshold, asking for the invoice only where the counts do not agree, and a clinical bill auditor signs each finding.
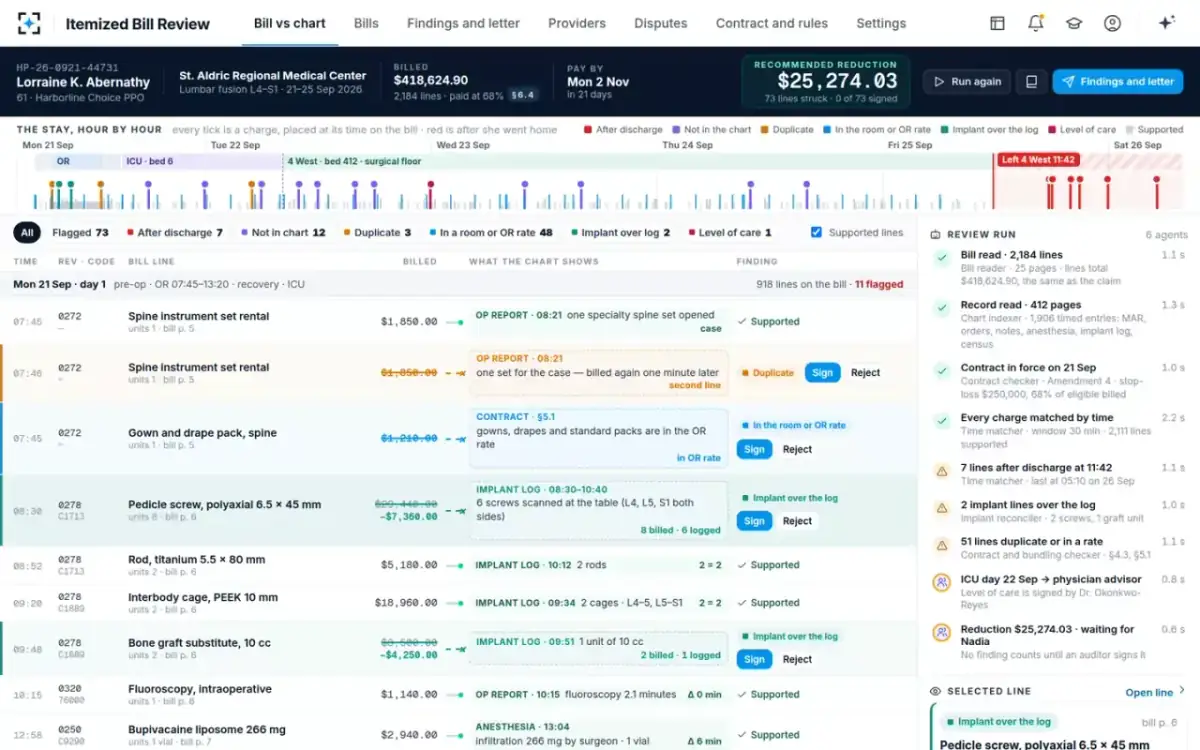
The figure below is the reconciliation for the spinal fusion in the solution's sample data: fictional hospital and patient, real arithmetic.
The device, three ways: implant log, billed line and invoice in Itemized Bill Review
Implant log: 6 scanned at the table: L4, L5, S1, both sides
On the bill: 8 units, $29,440.00
Invoice: Needed only if the hospital claims the 2 extra were opened and wasted
Result: 2 units removed, $7,360.00
Implant log: 2
On the bill: 2 units, $5,180.00
Invoice: Not needed: counts agree
Result: Supported
Implant log: 2: L4–L5 and L5–S1
On the bill: 2 units, $18,960.00
Invoice: Not needed: counts agree
Result: Supported
Implant log: 1 unit of 10 cc
On the bill: 2 units, $8,500.00
Invoice: Needed only with a wastage note
Result: 1 unit removed, $4,250.00
What is an implant invoice?
It is the purchase document for the device: the supplier, the item and catalogue number, often the lot or serial number, the quantity and the price the hospital paid, net of any discount or credit. In insurance claims, "implant invoice" and "implant sticker" often travel together: the sticker is the label from the device package, placed in the patient's record to identify exactly which device was implanted, and the invoice proves its cost.
The two answer different questions. The sticker, or the implant log built from scanning it, proves which devices went into this patient and how many. The invoice proves what each one cost the hospital. Neither is on the bill, which shows only the hospital's charge for each device, set from its own price list.
Why do insurers ask for implant invoices?
Insurers ask because the contract makes the hospital's cost matter. A hospital contract may carve implants out of the case rate and pay them separately, at the invoice cost plus a percentage, or at a percentage of charges with a cap tied to cost; under those terms the plan cannot price the line without the invoice. Even where implants are paid within a percentage of charges, the invoice is the evidence when a hospital bills more units than the log shows and says the extras were opened and wasted.
Charges and cost are far apart for devices. CMS's national average cost-to-charge ratio for implantable devices in fiscal year 2027 is 0.246 (FY 2027 IPPS final rule): the hospital's cost behind implant charges averages about a quarter of the charge. A contract that pays a high share of charges on implants is paying several times their cost, which is why carve-outs at invoice exist, and why a unit billed above the log is so expensive.
How are implants billed on a hospital bill?
As a supply line under an implant revenue code, with a device code and a unit count. CMS's instruction for outpatient claims names the catch-all: hospitals report implantable devices "under another revenue code such as 0278 – other implants" (CMS Program Memorandum A-03-035, 2003). Outpatient claims under Medicare's outpatient payment system must also carry the device's HCPCS code where one exists, and where none describes the device, "hospitals should report HCPCS code C1889 (Implantable/insertable device, not otherwise classified)" (Medicare Claims Processing Manual, ch. 4, §61.1).
On the itemized bill of an inpatient stay, the same coding usually appears line by line, because Medicare expects hospitals to bill every payer on the same basis. The sample bill shows pedicle screws, rods and an interbody cage under revenue code 0278 with device codes, units and a time in the operating room, which is what lets a reviewer put each line beside the implant log.
What counts as an implant, and what is a supply?
Not everything used in surgery is an implant, and the difference decides whether a line is separately payable. For a device to be reported as a device under Medicare's outpatient rules, it must, among other tests, "Be used for one patient only", "Be surgically implanted or inserted (either permanently or temporarily)", and not be "A material or supply furnished to a service (for example, a suture, customized surgical kit, scalpel, or clip, other than a radiological site marker)" (ch. 4, §61.1). Contracts draw their own lines; Medicare's is a useful place to start.
The sample bill has both kinds of error. Beside the implants, a spine instrument set is billed twice one minute apart, when the operative report records one set opened and the contract allows one per case, and a gown and drape pack is billed separately when the contract includes standard packs in the operating room rate. Neither is an implant question, but both sit in the same minutes of the bill and are found the same way: against the operative report and the contract.
Implants over the log, and an instrument set billed twice
The device, three ways: invoice, log and billed line
Reconcile in a fixed order: the log first, the bill second, the invoice only when needed. The log is the strongest evidence of what happened, because it is made at the table and the record must hold it: Medicare's conditions of participation require that "An operative report describing techniques, findings, and tissues removed or altered must be written or dictated immediately following surgery and signed by the surgeon" (42 CFR 482.51(b)(6)).
The log is about to get better. In its fiscal year 2027 inpatient rule, CMS finalized "the Unique Device Identifiers for Implantable Medical Devices measure beginning with the EHR reporting period in CY 2027", under which hospitals attest whether their electronic records capture "the complete Unique Device Identifier (UDI), which includes the device identifier and, when present on the device label, the production identifier, for each implantable medical device subject to UDI requirements" (91 FR 49570, 4 Aug 2026). A "No" answer is still allowed, so capture will spread unevenly; where it exists, the reviewer can match a billed line to a specific device, not just a count.
Two documents, two different questions about the same device
The implant invoice proves: What the hospital bought, by catalogue number and lot.
The implant log proves: What went into this patient, by label or device identifier, at what time.
The implant invoice proves: How many were bought, often in bulk, not per patient.
The implant log proves: How many were implanted, and, if recorded, how many were opened and wasted.
The implant invoice proves: The price paid, net of discounts and credits.
The implant log proves: Nothing about cost.
The implant invoice proves: When the contract pays at cost plus a markup, or when units above the log are claimed as waste.
The implant log proves: For every implant line: it is the count the bill is tested against.
What happens when a device is replaced under warranty?
The hospital may get the replacement free or with a credit, and Medicare then pays less. The regulation reduces the payment for a discharge when "A device is replaced without cost to the hospital", when the provider "received full credit for the cost of a device", or when "The provider receives a credit equal to 50 percent or more of the cost of the device" (42 CFR 412.89). Hospitals flag those claims with condition code 49 or 50 and report the credit amount under value code FD, which Medicare deducts from its payment for the listed DRGs.
The claims manual adds a rule about charges, not just payment: "If a hospital receives a credit for a replacement medical device, the charges to Medicare should also be appropriately reduced", citing the principle that "charges should be related consistently to the cost of the services and uniformly applied to all patients whether inpatient or outpatient" (Medicare Claims Processing Manual, ch. 3, §100.8). A commercial plan's contract may or may not adopt the same treatment; a plan that pays from charges has the stronger reason to ask.
How do manufacturer credits affect payment? What OIG found
They should cut it, and often have not. When HHS's Inspector General reviewed Medicare claims for recalled or prematurely failed cardiac devices, it found that "For 3,233 of the 6,558 Medicare claims that we reviewed, hospitals likely did not comply with Medicare requirements associated with reporting manufacturer credits", and that the cause was on the payer's side too: Medicare contractors "do not have a postpayment review process" to check (HHS-OIG, A-01-18-00502, November 2020).
Cardiac device replacements: what 911 hospitals were paid, and what they should have been
An earlier OIG audit in one region found the same pattern on a smaller scale: 191 claims with overpayments of $2.1 million "that the hospitals had not identified, refunded, or adjusted" by the time the audit began (HHS-OIG, A-09-15-02029, 2016). The lesson for a health plan is that credits do not appear on bills by themselves. A plan that pays implants from charges or at invoice needs a contract clause requiring credits to be passed through, and a reviewer who asks about them on replacement procedures.
What is implant cost plus reimbursement?
It is a contract term that pays implants separately at the hospital's invoice cost plus an agreed percentage, instead of including them in the case rate or paying them as a share of charges. Its appeal is that it ties payment to what the device actually cost. Its weakness is that it depends entirely on the invoice: the right invoice for the right device, at the net price after discounts, rebates and credits, for the units actually implanted.
Four checks make cost-plus terms work. The invoice must match the device in the log, not a similar one. The quantity paid must be the quantity implanted, with waste paid only where the contract says so and the record documents it. The price must be net of any credit or free replacement. And the markup must be applied once: a line billed at charges and then repriced at invoice plus markup should not also count toward a percentage-of-charges stop-loss. How carve-outs fit with the rest of a contract's payment terms is in high dollar claim review.
Implant contract terms, and what the reviewer must check under each
| Contract term | How the implant is paid | What the reviewer checks |
|---|---|---|
| Included in the case rate | Inside the fixed payment for the stay | Little to change, unless implant charges push the stay over a stop-loss threshold |
| Percentage of charges | A share of the billed implant charge | Units against the implant log; credits on replacements |
| Invoice cost plus a markup | Net invoice price plus an agreed percentage | Invoice matches the logged device; net of credits; units implanted; markup applied once |
| Stop-loss on the whole stay | A share of eligible charges once over the threshold | Units against the log, because every extra unit raises eligible charges |
Reconciling implants with Itemized Bill Review
In Itemized Bill Review, the implant reconciler compares each implant charge with the operative report's implant log, by item and count, and with invoices when asked. Its one hard limit is written into it: it never accepts units above the log without an invoice and a wastage note. A line over the log becomes a finding with the log page cited, and the clinical bill auditor signs or rejects it; the contract checker separately applies the operating room and instrument clauses that catch duplicate sets and bundled packs.
The checklist below is what the reconciliation needs from the hospital, in the order the reviewer uses it. How to test whether a product actually does this, by planting an over-count in a closed bill, is in medical bill review software, tested.
What an implant reconciliation needs, and in what order
- The operative report and implant log
Device, count and time, scanned or written at the table; device identifiers where captured.
- The bill’s implant lines
Revenue code, device code, units, amount and time, tied to the claim.
- The contract term for implants on the date of service
Case rate, share of charges, cost plus markup, or stop-loss; the amendment in force.
- The invoice, when the term or the counts require it
Net of discounts and credits, for the device in the log.
- A wastage note, for any unit opened but not implanted
Recorded in the operative record, not added to the bill later.
- Credit status on replacements
For a device replaced under warranty or recall, whether a credit was received and how much.
Questions people ask
What is an implant invoice in medical billing?
It is the supplier's invoice for a device implanted during a procedure, used to support the hospital's implant charge or to price it under a cost-plus contract. Insurers usually ask for it with the implant sticker or log that identifies the device in the patient's record.
What is revenue code 278?
Revenue code 0278 is the code hospitals use for "other implants" on UB-04 claims, as CMS's 2003 instruction on reporting implantable devices describes it. On an outpatient Medicare claim, the line must also carry the device's HCPCS code, or C1889 when no specific code exists.
What is an implant log?
The record, usually part of the operative report, of every device implanted during surgery: what it was, how many, and when, often scanned from the package label at the table. It is the count a reviewer tests the bill against.
Can a hospital bill for an implant that was opened but not used?
Only if the contract allows it and the record documents the waste at the time. In Itemized Bill Review, units above the implant log are never accepted without an invoice and a wastage note.
Do manufacturer credits reduce what a commercial plan pays?
Only if the contract says so or the plan's payment is tied to cost. Medicare reduces its payment for credits of 50% or more and expects charges to be reduced too; a commercial plan should write a pass-through clause into its contracts.